Can AFib come and go?
Yes. AFib often comes and goes. Atrial fibrillation is an irregular, often fast heart rhythm that starts in the heart’s upper chambers. When episodes start and stop on their own within seven days, doctors call it paroxysmal AFib. Even when the rhythm returns to normal, the condition is still present and needs a full evaluation.
In a normal heartbeat, a small natural pacemaker sends steady electrical signals that make the upper chambers (the atria) squeeze in rhythm. In AFib, disorganized signals make the atria quiver instead. The lower chambers then beat irregularly, and often too fast. Learn more on our atrial fibrillation page.
- Episode: a stretch of time when the heart is in AFib. It can last seconds, hours, or days.
- Sinus rhythm: sinus rhythm is the heart’s normal, steady rhythm. Between episodes of paroxysmal AFib, most people are back in sinus rhythm.
- Symptoms during an episode: a fluttering or pounding heartbeat, tiredness, shortness of breath, dizziness, or chest discomfort. Some people feel nothing at all.
- Silent AFib: AFib that causes no symptoms. It is often found by chance on an EKG, a smartwatch, or a pacemaker check.
Because symptoms can be mild or missing, how you feel is not a reliable guide to how often your heart is in AFib. Our guide to AFib symptoms and irregular heartbeat covers the warning signs in more detail.
Alliance Heart & Vascular
Expert heart care that keeps you moving.
Three board-certified cardiologists work as one team to find the cause of your symptoms and build a clear plan for your heart health.
- Dr. Rizwan KhanMD, FACC
- Dr. Muhammad Waheed RajaMD, FACC, FASE
- Dr. Afaq MotiwalaMD, FACC, RPVI
What is the difference between paroxysmal, persistent, and permanent AFib?
The main difference is how long episodes last. Paroxysmal AFib stops on its own within seven days. Persistent AFib lasts longer than seven days and usually needs treatment to stop. Long-standing persistent AFib lasts more than a year. Permanent AFib means you and your doctor have decided to stop trying to restore a normal rhythm.
| Type | What it means | Typical goal of care |
|---|---|---|
| Paroxysmal AFib | Episodes start suddenly and stop on their own or with treatment within seven days, often within hours. | Reduce episodes, judge stroke risk, and consider rhythm control early |
| Persistent AFib | AFib lasts longer than seven days without stopping on its own. | Restore normal rhythm with medicine, cardioversion, or ablation, or control the heart rate |
| Long-standing persistent AFib | AFib has been continuous for more than 12 months. | Rhythm control is still possible for some patients but is harder |
| Permanent AFib | A shared decision to stop trying to restore normal rhythm. | Control the heart rate and prevent stroke |
The 2023 ACC/AHA atrial fibrillation guideline also describes AFib as a disease that moves through stages, from being at risk, to early warning changes, to AFib itself, and finally to permanent AFib. This view stresses that AFib is not a one-time event but a long-term condition that can be slowed down.
- Cardioversion: cardioversion is a treatment that resets the heart to a normal rhythm, usually with a brief, controlled electrical shock while you are sedated.
- Rate control: rate control means using medicine to keep the heart from beating too fast, even if the rhythm stays irregular.
- Rhythm control: rhythm control means using medicine, cardioversion, or ablation to bring back and keep a normal rhythm.
Why does AFib start and stop on its own?
AFib starts when extra electrical signals, often from tissue near the veins that drain into the heart, set off chaotic beating in the upper chambers. It stops when the heart’s normal pacemaker takes back control. Triggers such as alcohol, poor sleep, illness, and stress make it easier for an episode to start and keep going.
The pulmonary veins are the four blood vessels that carry oxygen-rich blood from the lungs into the left upper chamber of the heart. Muscle fibers around these veins can fire early signals. Whether those signals turn into a full episode depends on the condition of the atria and the nervous system at that moment. That is why episodes can cluster for a few weeks and then disappear for months.
- Alcohol: even moderate drinking can trigger episodes, and binge drinking is a well-known cause.
- Sleep apnea: obstructive sleep apnea is a sleep disorder in which the airway repeatedly closes during sleep, lowering oxygen and straining the heart.
- Illness and fever: infections, surgery, and dehydration can set off AFib.
- High blood pressure: years of high pressure stretch and stiffen the atria. See our high blood pressure page.
- Thyroid problems: an overactive thyroid speeds the heart and can trigger AFib.
- Stimulants: some decongestants, diet pills, and recreational drugs raise the heart rate.
- Nighttime nerve changes: the vagus nerve slows the heart during rest, and shifts in its activity can start episodes at night. Read more in our article on heart palpitations at night.
Does AFib that comes and goes still raise stroke risk?
Yes. AFib that comes and goes can still cause a stroke. During AFib, blood can pool and clot in the upper chambers, and a clot can travel to the brain. Doctors base the decision about blood thinners on your personal risk score, such as age and health conditions, not on how often episodes happen.
According to the CDC, AFib raises the risk of stroke about five times. Strokes caused by AFib tend to be more severe than other strokes. The good news is that blood thinners lower this risk a great deal for people who need them.
- CHA₂DS₂-VASc score: the CHA₂DS₂-VASc score is a simple point system doctors use to estimate stroke risk in AFib. Points are added for heart failure, high blood pressure, age, diabetes, prior stroke, vascular disease, and female sex.
- Anticoagulant: an anticoagulant, or blood thinner, is a medicine that lowers the blood’s ability to form clots. It does not stop AFib, but it helps prevent strokes.
- Bleeding risk: your cardiologist also weighs your risk of bleeding before recommending a blood thinner.
- Left atrial appendage: the left atrial appendage is a small pouch in the left upper chamber where most AFib clots form. Some patients who cannot take blood thinners long term are evaluated for a procedure to close it.
One of the most dangerous mistakes is stopping a prescribed blood thinner because episodes seem to have stopped. Your stroke risk comes mostly from your age and health history, which do not change when your rhythm is quiet.
Had an episode of AFib that went away on its own?
Our board-certified cardiologists can check your stroke risk, record your rhythm with a wearable monitor, and build a treatment plan. Testing is often done on site at our Pearland office.
Does intermittent AFib get worse over time?
It often does. Without treatment, paroxysmal AFib tends to happen more often and last longer, and many people move on to persistent AFib. Each episode can cause changes in the heart’s upper chambers that make the next episode easier. Treating risk factors and the rhythm early can slow this progression and lower your AFib burden.
AFib burden is the share of time your heart spends in AFib over a set period, such as a day or a month. A wearable monitor can measure it. Doctors track burden because a rising burden often signals that the condition is progressing.
- Atrial remodeling: atrial remodeling is the gradual stretching, scarring, and electrical change in the upper chambers that makes AFib more likely to keep going.
- Risk factors that speed progression: high blood pressure, obesity, sleep apnea, diabetes, heavy alcohol use, and heart valve disease.
- Heart failure risk: long periods of fast, irregular beating can weaken the heart muscle. Learn more on our heart failure page.
- Why early care matters: rhythm treatments such as catheter ablation tend to work best when AFib is still paroxysmal.
When is an AFib episode an emergency?
An AFib episode is an emergency when it comes with chest pain or pressure, fainting, severe shortness of breath, confusion, or any sign of stroke, such as face drooping, arm weakness, or trouble speaking. Call 911 right away. Do not drive yourself, and do not wait to see whether the episode stops on its own.
Call 911 now if an irregular heartbeat comes with:
- Stroke signs: sudden face drooping, arm or leg weakness, slurred speech, or confusion
- Chest pain, pressure, or tightness
- Fainting or feeling like you are about to pass out
- Severe shortness of breath, especially when lying flat
- A very fast heartbeat that does not settle after several minutes of rest
Some situations are not emergencies but need a prompt call to your cardiologist:
- First episode: a first-ever episode of irregular heartbeat, even if it has stopped.
- Longer episodes: episodes lasting longer than usual or coming more often.
- New symptoms: new swelling in the legs, tiredness, or breathlessness between episodes.
When should you see a cardiologist for AFib that comes and goes?
See a cardiologist after any confirmed episode of AFib, even a single short one that stopped on its own. You should also book a visit if episodes return, last longer, or come more often, if a smartwatch keeps flagging an irregular rhythm, or if you stopped a blood thinner because you felt better.
A cardiologist is a physician who specializes in the heart and blood vessels. Use this checklist to decide whether it is time to book:
- Confirmed AFib: any EKG or monitor that has shown AFib, even once.
- Recurring palpitations: bouts of irregular heartbeat that start and stop on their own. See our heart palpitations page.
- Changing pattern: episodes that are getting longer or more frequent.
- Wearable alerts: repeated irregular rhythm notifications from a watch or fitness tracker.
- Risk factors: high blood pressure, diabetes, sleep apnea, heart failure, or age 65 or older.
- Medicine questions: you are unsure whether you need a blood thinner, or you stopped one on your own.
- Upcoming surgery: a planned procedure when you have a history of AFib.
How do cardiologists diagnose AFib that comes and goes?
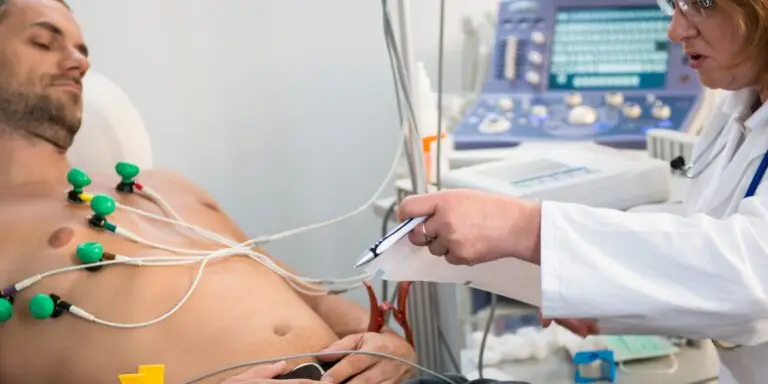
Cardiologists diagnose intermittent AFib by recording the heart rhythm during an episode. Because episodes come and go, a single EKG is often normal, so many patients wear a heart monitor for one to 30 days. An echocardiogram, blood tests, and sleep apnea screening help find the causes and guide stroke prevention.
How an intermittent AFib evaluation usually works
- ListenYour cardiologist reviews your episodes, triggers, symptoms, and health history.
- RecordAn EKG and a wearable monitor capture episodes and measure your AFib burden.
- ScoreYour stroke and bleeding risk are scored to decide on a blood thinner.
- PlanYou get a plan for risk factors, symptoms, and rhythm control.
| Test | What it is | What it helps find |
|---|---|---|
| EKG | An EKG (electrocardiogram) is a quick, painless test that records the heart’s electrical activity through stickers on the chest. | AFib if it is happening during the test, plus signs of heart strain |
| Holter monitor | A Holter monitor is a small wearable recorder that tracks every heartbeat for 24 to 48 hours or longer. | Frequent episodes and AFib burden |
| Patch or event monitor | A patch or event monitor is a wearable device worn for up to about 30 days that records the rhythm continuously or when you press a button. | Episodes that happen a few times a week or less |
| Implantable loop recorder | An implantable loop recorder is a tiny device placed under the skin of the chest that records the rhythm for years. | Rare episodes or unexplained stroke |
| Echocardiogram | An echocardiogram is an ultrasound test that shows the heart’s chambers, valves, and pumping strength. | Enlarged atria, valve disease, or a weak heart muscle |
| Blood tests | Lab tests for thyroid hormone, kidney function, electrolytes, and blood count. | Thyroid problems and other treatable triggers |
| Sleep apnea screening | Questions and, if needed, a sleep study that measures breathing during sleep. | Sleep apnea, a common and treatable driver of AFib |
Smartwatch alerts can be a helpful early warning, but a doctor needs to confirm AFib on a medical-grade recording. Bring any saved watch ECG strips to your visit. See all of our cardiac diagnostic testing services.
How is AFib that comes and goes treated?
Treatment for intermittent AFib has four parts: preventing stroke with a blood thinner when your risk score calls for it, treating risk factors such as weight, alcohol, blood pressure, and sleep apnea, controlling symptoms with medicine, and restoring normal rhythm. For some patients, catheter ablation is an early option that can reduce or stop episodes.
| Treatment | What it does |
|---|---|
| Blood thinner | Lowers stroke risk when your risk score is high enough. It is taken every day, not only during episodes. |
| Risk factor control | Weight loss, less alcohol, regular exercise, blood pressure control, and sleep apnea treatment can reduce how often AFib returns. |
| Rate-control medicine | Keeps the heart from racing during episodes so you feel better. |
| Rhythm-control medicine | Antiarrhythmic drugs, which are medicines that help keep a normal rhythm, can reduce episodes. |
| Catheter ablation | A procedure that blocks the faulty signals, often around the pulmonary veins. It works best in paroxysmal AFib. |
Catheter ablation is a minimally invasive procedure that uses heat or cold energy, delivered through thin tubes placed in a vein, to create tiny scars that block the signals causing AFib. The 2023 ACC/AHA guideline supports ablation as a first-line choice for selected patients with symptomatic paroxysmal AFib. When ablation is right for you, our team refers you to an electrophysiologist, a cardiologist who specializes in heart rhythm procedures, and continues your long-term care afterward. Never start, stop, or change a heart medicine on your own.
What can you do to have fewer AFib episodes?
You can lower how often AFib comes back by cutting back on alcohol, losing extra weight, staying active, controlling your blood pressure, treating sleep apnea, and taking medicines exactly as prescribed. Keeping a log of each episode helps your cardiologist spot triggers. These steps support medical care but do not replace a stroke-risk evaluation.
- Cut back on alcohol: drinking less, or not at all, is one of the most effective steps patients can take.
- Lose extra weight: studies show that steady weight loss can reduce AFib episodes in people who are overweight.
- Move most days: regular moderate exercise, such as brisk walking, supports heart health.
- Control blood pressure: check it at home and follow your treatment plan. Our preventive cardiology team can help.
- Take snoring seriously: ask about sleep apnea testing if you snore loudly or wake up tired.
- Log every episode: write down the date, start and end time, what you were doing, and how you felt.
- Keep taking your blood thinner: never stop it because episodes seem to have stopped.
Where can you get AFib care in Pearland and Downtown Houston?
Alliance Heart & Vascular evaluates and treats AFib that comes and goes at its Pearland office, with Downtown Houston coming soon. Board-certified cardiologists Dr. Rizwan Khan, Dr. Muhammad Waheed Raja, and Dr. Afaq Motiwala provide evidence-based rhythm monitoring, stroke-risk scoring, and long-term care. New patients are welcome. Call (346) 614-0002 to schedule a visit.
- Dr. Rizwan Khan, MD, FACC: board certified in cardiovascular disease, echocardiography, and nuclear cardiology, with fellowship training at Loyola University Medical Center. He cares for patients with high blood pressure, chest pain, coronary artery disease, and heart failure.
- Dr. Muhammad Waheed Raja, MD, FACC, FASE: board certified in cardiovascular disease and internal medicine, with fellowship training at Tulane University School of Medicine. He focuses on preventive cardiology and non-invasive cardiac imaging.
- Dr. Afaq Motiwala, MD, FACC, RPVI: board certified in interventional cardiology, cardiovascular disease, endovascular medicine, and internal medicine, with more than 14 years of experience in general and interventional cardiology.
Pearland
10905 Memorial Hermann Drive, Suite 203
Pearland, TX 77584
Monday–Friday, 8:00 a.m.–4:30 p.m.
Downtown Houston Coming Soon
Will serve the Texas Medical Center, Midtown, and Downtown Houston.
Call (346) 614-0002 for opening updates. Patients are seen in Pearland now.
Our general cardiology team coordinates testing, follow-up, and referral to an electrophysiologist when ablation is the next step. See our new patient information or contact us with questions.
What are the key takeaways about AFib that comes and goes?
AFib that comes and goes is called paroxysmal AFib, and it is still a real heart rhythm condition. It can raise stroke risk even between episodes, and it often gets worse over time without care. A cardiologist can record your rhythm, score your stroke risk, and start treatment early, when it tends to work best.
- Stopping is not curing: an episode ending does not mean AFib is gone.
- Stroke risk is personal: blood thinner decisions depend on your risk score, not how often episodes happen.
- AFib can progress: episodes often grow longer and more frequent over the years.
- Risk factors matter: less alcohol, weight loss, and treating sleep apnea and blood pressure can reduce episodes.
- Help is local: board-certified cardiologists in Pearland can test and treat AFib.
What other questions do patients ask about AFib that comes and goes?
Patients often ask whether AFib can go away for good, how long episodes last, whether they need a blood thinner, whether ablation can cure it, and what to do during an episode. The short answers below reflect current cardiology guidance. Your own answer depends on your symptoms, health history, and rhythm testing results.
Can AFib go away on its own forever?
Single episodes often stop on their own, but the tendency to have AFib rarely disappears. Some people go months or years between episodes, especially after treating triggers such as alcohol, weight, and sleep apnea. Ongoing follow-up is still important.
How long do paroxysmal AFib episodes last?
By definition, paroxysmal episodes stop within seven days. Many last from a few minutes to several hours. Episodes that last longer than seven days are classified as persistent AFib.
If my AFib comes and goes, do I need a blood thinner?
Maybe. The decision depends on your stroke risk score, which counts factors such as age, high blood pressure, diabetes, heart failure, and prior stroke. People with intermittent AFib can need a blood thinner just as much as people with constant AFib.
What should I do during an AFib episode?
Sit down, rest, and note the time and how you feel. If your doctor has given you an action plan, follow it. Call 911 if you have chest pain, fainting, severe shortness of breath, or stroke signs.
Can paroxysmal AFib turn into permanent AFib?
Yes, it can. Over time, many people move from paroxysmal to persistent AFib, and some reach permanent AFib. Treating risk factors and considering rhythm control early can help slow this progression.
Will catheter ablation cure AFib that comes and goes?
Ablation works best in paroxysmal AFib and stops or greatly reduces episodes for many patients, though some need a repeat procedure. It is not a guaranteed cure, and the decision is made with a heart rhythm specialist after testing.
Can I stop my blood thinner if I have not had an episode in months?
No, not on your own. Your stroke risk comes mostly from your age and health conditions, not from recent episodes. Only change a blood thinner after talking with your cardiologist.
Can a smartwatch detect AFib that comes and goes?
Many smartwatches can flag a possible irregular rhythm and record a short ECG strip. These alerts are useful, but a doctor must confirm AFib with an EKG or a medical-grade heart monitor.
Get answers about AFib that comes and goes
An episode that stopped on its own still deserves a plan. Schedule an evaluation with Dr. Rizwan Khan, Dr. Muhammad Waheed Raja, or Dr. Afaq Motiwala at our Pearland office (Downtown Houston coming soon). Call (346) 614-0002 or request an appointment online.
Sources and further reading
- 2023 ACC/AHA/ACCP/HRS Guideline for the Diagnosis and Management of Atrial Fibrillation, Circulation.
- About Atrial Fibrillation, Centers for Disease Control and Prevention.
- Atrial Fibrillation, National Heart, Lung, and Blood Institute.
- Atrial Fibrillation: Treatment, National Heart, Lung, and Blood Institute.
- Atrial Fibrillation, MedlinePlus, U.S. National Library of Medicine.
- Sleep Apnea, National Heart, Lung, and Blood Institute.